

AI generated
Apr 8, 2026, 14:17
Chokri Ben Lamine: Anticoagulation Switching Pearls
Chokri Ben Lamine, Adult Hematology and SCT Assistant Consultant at Oncology Center of Excellence at King Faisal Specialist Hospital and Research Center, shared a post on X:
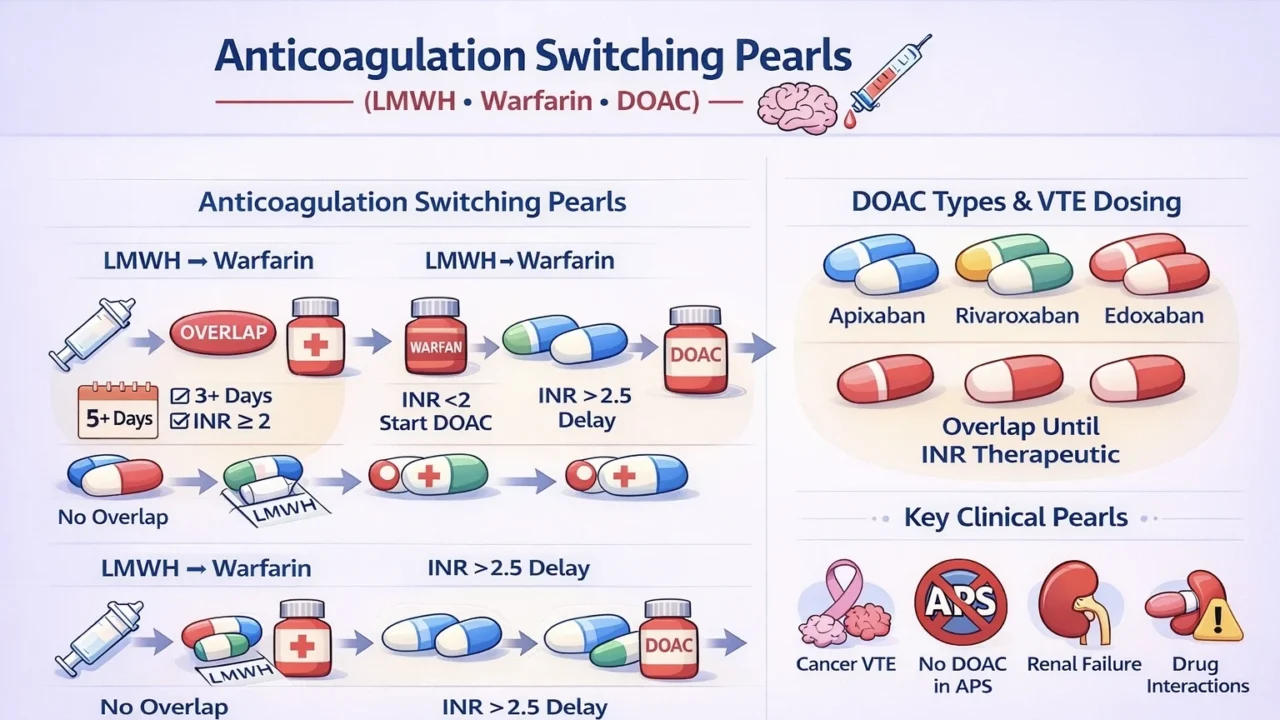
“Anticoagulation Switching Pearls (LMWH to Warfarin to DOAC)
LMWH to Warfarin – Overlap is mandatory:
- At least 5 days and INR at least 2 for 24–48 hours
- Prevent early hypercoagulability (decreased Protein C)
Start warfarin at 2–5 mg, adjust according to INR
Stop LMWH only when INR is stable and therapeutic
LMWH and DOAC
- Switching from LMWH to DOAC: Start DOAC at the time of the next LMWH dose; no overlap
- Switching from DOAC to LMWH: Start LMWH at the time of the next DOAC dose; no overlap
Warfarin to DOAC
- If INR is less than 2, start DOAC immediately
- If INR is 2 to 2.5, start on the same day
- If INR is greater than 2.5, delay
DOAC to Warfarin
- Overlap DOAC with warfarin
- Stop DOAC once INR is therapeutic
DOAC VTE Dosing in Adults
Apixaban
- Acute VTE: 10 mg BID for 7 days
- Then 5 mg BID
- Extended 2.5 mg BID
- Least bleeding risk, preferred in many hematology patients
Rivaroxaban
- Acute VTE: 15 mg BID for 21 days
- Then 20 mg once daily
- Extended 10 mg once daily
- Take with food
Edoxaban
- Requires lead-in LMWH for 5 to 10 days
- Then 60 mg once daily
- Reduce to 30 mg if weight 60 kg or less or CrCl 15 to 50
Dabigatran
- Requires LMWH lead-in for 5 to 10 days
- Then 150 mg BID
- Avoid if CrCl less than 30
- Higher gastrointestinal side effects
Key Clinical Pearls
- Only dabigatran and edoxaban need LMWH lead-in
- Apixaban and rivaroxaban follow a single-drug approach
Cancer-associated VTE
- DOAC such as apixaban or rivaroxaban preferred
- Use LMWH if gastrointestinal or genitourinary bleeding risk
APS triple positive
- Avoid DOAC; use warfarin
Renal failure
- Prefer warfarin if severe CKD
Drug interactions
- DOAC affected by P-gp and CYP3A4 inhibitors such as azole, chemotherapy, tyrosine kinase inhibitors
Bridging rule
- Warfarin requires overlap
- DOAC requires timing switch with no overlap.”
Stay updated with Hemostasis Today.
-
Nov 15, 2026, 23:44Pablo César Spada: Prevention of Venous Thromboembolism After Total Hip or Knee Replacement
-
Nov 15, 2026, 23:30Eshal Amir: Factor XI Inhibitors in AFib and Aortic Mortality Trends
-
Nov 15, 2026, 23:19Hamza Bashir: Adding Endovascular Therapy to Anticoagulation Cuts Moderate-to-Severe PTS in Half
-
Nov 15, 2026, 23:06Lanre Tunji-Ajayi: 2 Days of Deliberative Dialogue Hosted by the Network of Rare Blood Disorder Organizations
-
Nov 15, 2026, 23:00Fanny Delettre: Looking Back at Volunteer Blood Donor Friends Day
-
Nov 15, 2026, 20:56Victoria Adedoyin Adisa-Thomas: What I Learned About SCD During My Genetic Counselling Rotation
-
Nov 15, 2026, 20:55Martin Holst Lange: One Step Closer to a Potential New Treatment for Sickle Cell Disease
-
Nov 15, 2026, 20:53Bontha Babu: Health-Related Quality of Life Among Adults with Sickle Cell Disease in India
-
Nov 15, 2026, 20:52Miguel Ángel Herrera Rojas: A First-Line ITP Approach Presented at ASH in 2013 Now Reflected in the 2026 Guidelines