


Heghine Khachatryan: What Should We Test From a Hematologic Perspective in Young Cryptogenic Stroke?
Heghine Khachatryan, Editor-in-Chief of Hemostasis Today, Head of Hemophilia and Thrombosis Center at Yeolyan Hematology and Oncology Center, shared a post on LinkedIn:
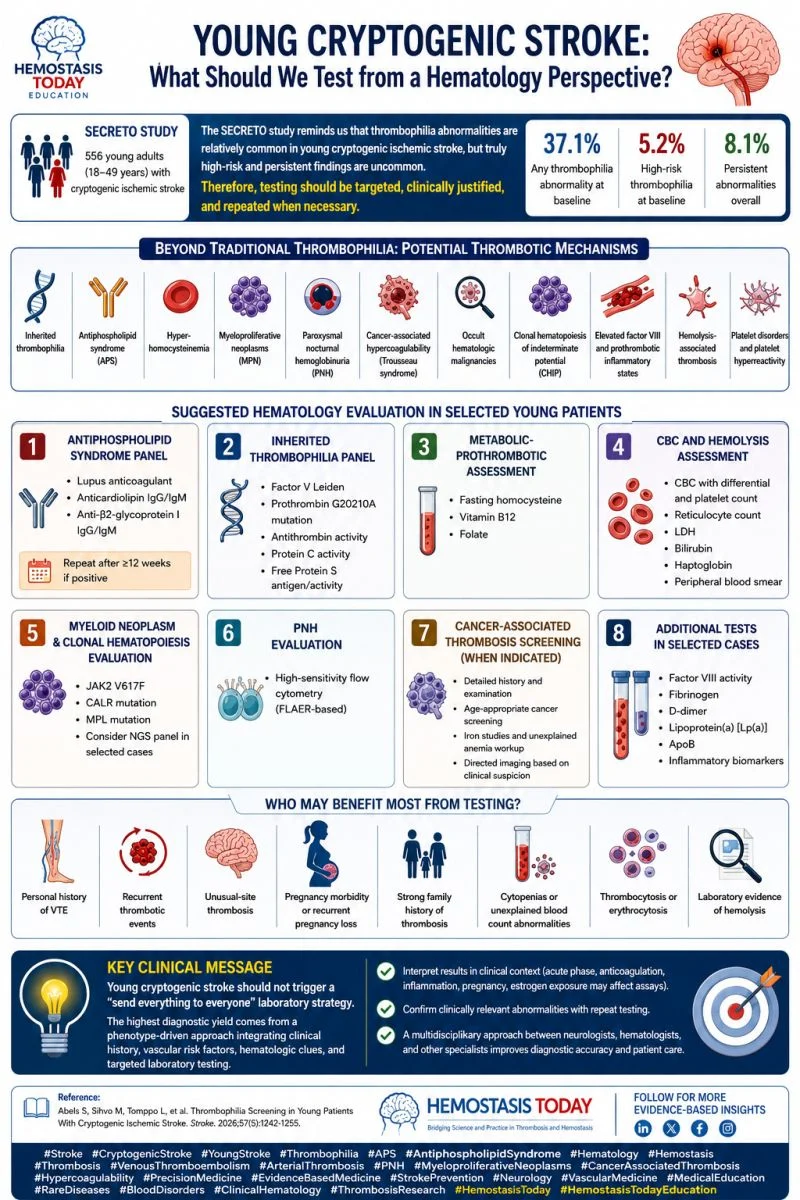
“Young Cryptogenic Stroke: What Should We Test from a Hematology Perspective?
The SECRETO study demonstrated that thrombophilia abnormalities are relatively common in young patients with cryptogenic ischemic stroke; however, truly high-risk and persistent abnormalities are uncommon.
These findings support a targeted and clinically driven approach to hematologic evaluation.
Potential hematologic contributors to young cryptogenic stroke include inherited thrombophilia, antiphospholipid syndrome, hyperhomocysteinemia, myeloproliferative neoplasms, paroxysmal nocturnal hemoglobinuria, cancer-associated hypercoagulability, clonal hematopoiesis, elevated factor VIII, hemolysis-associated thrombosis, platelet disorders, and rare fibrinolytic abnormalities.
A reasonable hematologic evaluation in selected patients may include:
- Antiphospholipid antibodies (lupus anticoagulant, anticardiolipin antibodies, anti-β2 glycoprotein I antibodies)
- Inherited thrombophilia testing (Factor V Leiden, Prothrombin G20210A, antithrombin, protein C, protein S)
- Homocysteine, vitamin B12, and folate
- Complete blood count, peripheral blood smear, reticulocytes, LDH, bilirubin, and haptoglobin
- JAK2 V617F, CALR, and MPL mutation analysis when myeloproliferative neoplasms are suspected
- High-sensitivity flow cytometry for PNH when clinically indicated
- Age-appropriate evaluation for occult malignancy
- Selected biomarkers including factor VIII, fibrinogen, D-dimer, lipoprotein(a), and ApoB
Testing is most informative in young patients with recurrent thrombosis, venous thromboembolism, unusual-site thrombosis, pregnancy morbidity, strong family history of thrombosis, unexplained cytopenias, thrombocytosis, erythrocytosis, or laboratory evidence of hemolysis.
The highest diagnostic yield comes not from indiscriminate testing but from a phenotype-driven strategy integrating clinical history, vascular risk factors, and targeted laboratory investigation.”
Other posts featuring Heghine Khachatryan on Hemostasis Today.
-
Sep 17, 2026, 20:19Riten Kumar: Boston Children’s Hospital Ranked No. 1 in Seven Pediatric Specialties
-
Sep 17, 2026, 20:17Katrina Snow: Whole Blood or Component Therapy – Which Would You Choose?
-
Sep 17, 2026, 16:30Daria Camilli: Empowering Bleeding Disorder Advocacy Through Health Economics
-
Sep 17, 2026, 16:17Mehran Ghasemzadeh: Platelet NK Cell Crosstalk in Advanced Coronary Artery Disease
-
Sep 17, 2026, 16:16Barbara Adams Krolak: Do GLP-1s Affect Blood Clot Risk?
-
Sep 17, 2026, 15:46Heghine Khachatryan: Clinical Context at the Core of Thrombosis and Thrombophilia Management
-
Sep 17, 2026, 15:33Alexandros Makis: When Microcytic Anemia Has an Inherited Cause
-
Sep 17, 2026, 15:22α2-Antiplasmin Inhibition and the Future of Thrombolysis
-
Sep 17, 2026, 15:20Fatma M. Attia: Expanding the Evidence Base for Therapeutic Plasma Exchange Across Multiple Indications