


Fredrick Chalinga: Microcytic Anemia Does Not Always Mean Iron Deficiency
Fredrick Chalinga, Medical Technologist at Aga Khan University Hospital, shared a post on LinkedIn:
“Microcytic Anemia does not always mean iron deficiency.
One of the most important distinctions in hematology is differentiating between Iron Deficiency Anemia (IDA) and thalassemia trait.
Both can present with:
Low MCV, microcytosis, and hypochromia
Yet their causes, clinical implications, and management are completely different.
Confusing the two may lead to:
- Missed diagnoses
- Unnecessary iron therapy
- Delayed genetic counseling
- Inappropriate transfusion decisions.
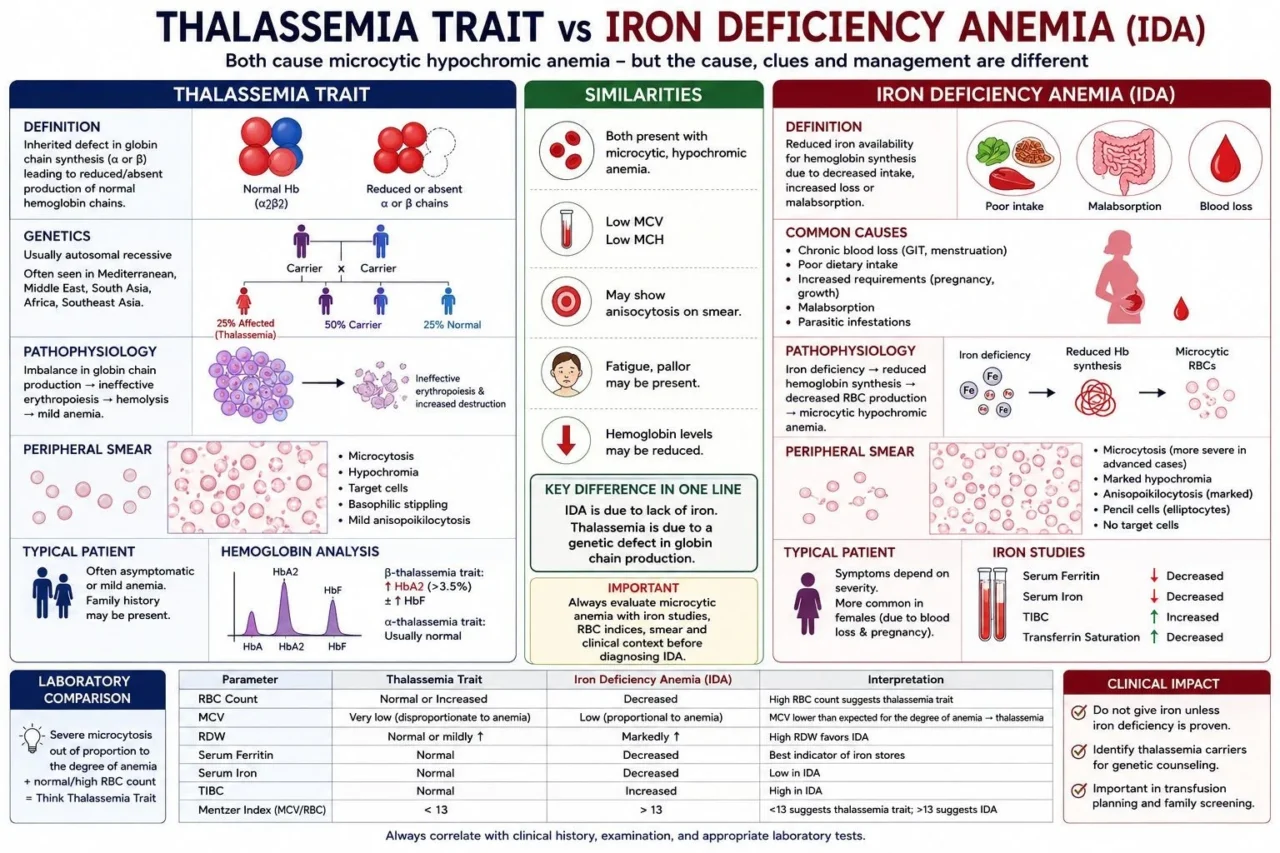
Similarities between IDA and Thalassemia:
- Both commonly produce microcytic hypochromic anemia
- Both may show anisocytosis on smear
- Fatigue and pallor may occur in both conditions
- Reduced hemoglobin levels can be present
- Peripheral blood film may initially appear similar
But the underlying mechanisms differ greatly.
Iron Deficiency Anemia (IDA) IDA occurs because the body lacks sufficient iron to produce hemoglobin.
Common causes: Chronic blood loss, poor dietary intake, pregnancy, malabsorption, parasitic infestations
Typical laboratory findings include low serum ferritin, low serum iron, high TIBC, increased RDW, low RBC count
Peripheral smear depicts pencil cells, marked anisopoikilocytosis, hypochromia, and progressive microcytosis
Thalassemia Trait Thalassemia is an inherited defect in globin chain synthesis, not an iron problem.
Typical findings: Very low MCV despite mild anemia, normal iron studies, normal or high RBC count, target cells on smear, mild anisocytosis and elevated HbA₂ in β-thalassemia trait
Important laboratory clues
IDA:
Low RBC count, High RDW, Ferritin decreased
Thalassemia trait: RBC count is often normal/high, RDW often normal or mildly raised, ferritin normal, microcytosis may appear disproportionate to anemia severity
Clinical insight: A patient with severe microcytosis but relatively preserved hemoglobin and a high RBC count should immediately raise suspicion for thalassemia trait.
Meanwhile, progressive iron deficiency usually shows worsening anisocytosis and declining ferritin levels.
Why this distinction matters: Giving iron to a thalassemia patient without iron deficiency offers little benefit and may contribute to iron overload over time.
The CBC alone is not enough.
Correlation with: Iron studies, blood film, RBC indices, and hemoglobin electrophoresis is essential for accurate diagnosis.
Key takeaway: All microcytic anemia is not iron deficiency.
The microscope, RBC count, RDW, and iron profile together help uncover the true diagnosis.
Have you encountered cases where the thalassemia trait was initially mistaken for iron deficiency anemia?”
Stay updated with Hemostasis Today.
-
Sep 20, 2026, 13:29Factor XI Deficiency and the Challenge of Unpredictable Bleeding – EHC
-
Sep 20, 2026, 13:18Cindy Howry: FDA Approves First Treatment for Ataxia-Telangiectasia
-
Sep 20, 2026, 13:08Mohammad Salar Amoli: When Routine Coagulation Tests Miss von Willebrand Disease
-
Sep 20, 2026, 12:55Stelios Andreadis։ Human Salivary Gland Organoids Offer New Potential for Regenerative Medicine
-
Sep 20, 2026, 12:43Obi Light Ogbonnia: The Power of Lived Experience in Sickle Cell Care
-
Sep 20, 2026, 12:34Sabrine Mekni: Advancing HSCT for Children With Fanconi Anemia
-
Sep 20, 2026, 12:11Giacomo Buso: Silent Atherosclerosis Begins Earlier Than Expected
-
Sep 20, 2026, 12:0310 Posts Not to Miss This Week
-
Sep 20, 2026, 11:27Edward Lee Carter: Prasugrel Dosing Matters in P2Y12 Inhibitor Comparisons After PCI