


Edward Lee Carter: In Antithrombotic Therapy, “More Protection” Can Become More Harm Surprisingly Quickly
Edward Lee Carter, Clinical Pharmacist Practitioner at U.S. Department of Veterans Affairs, shared on LinkedIn:
“In antithrombotic therapy, ‘more protection’ can become more harm surprisingly quickly.
Patients with atrial fibrillation who experience an acute MI and undergo PCI present a difficult therapeutic collision:
- AF creates an indication for anticoagulation.
- ACS and coronary stenting create an indication for antiplatelet therapy.
- Combining them increases bleeding risk.
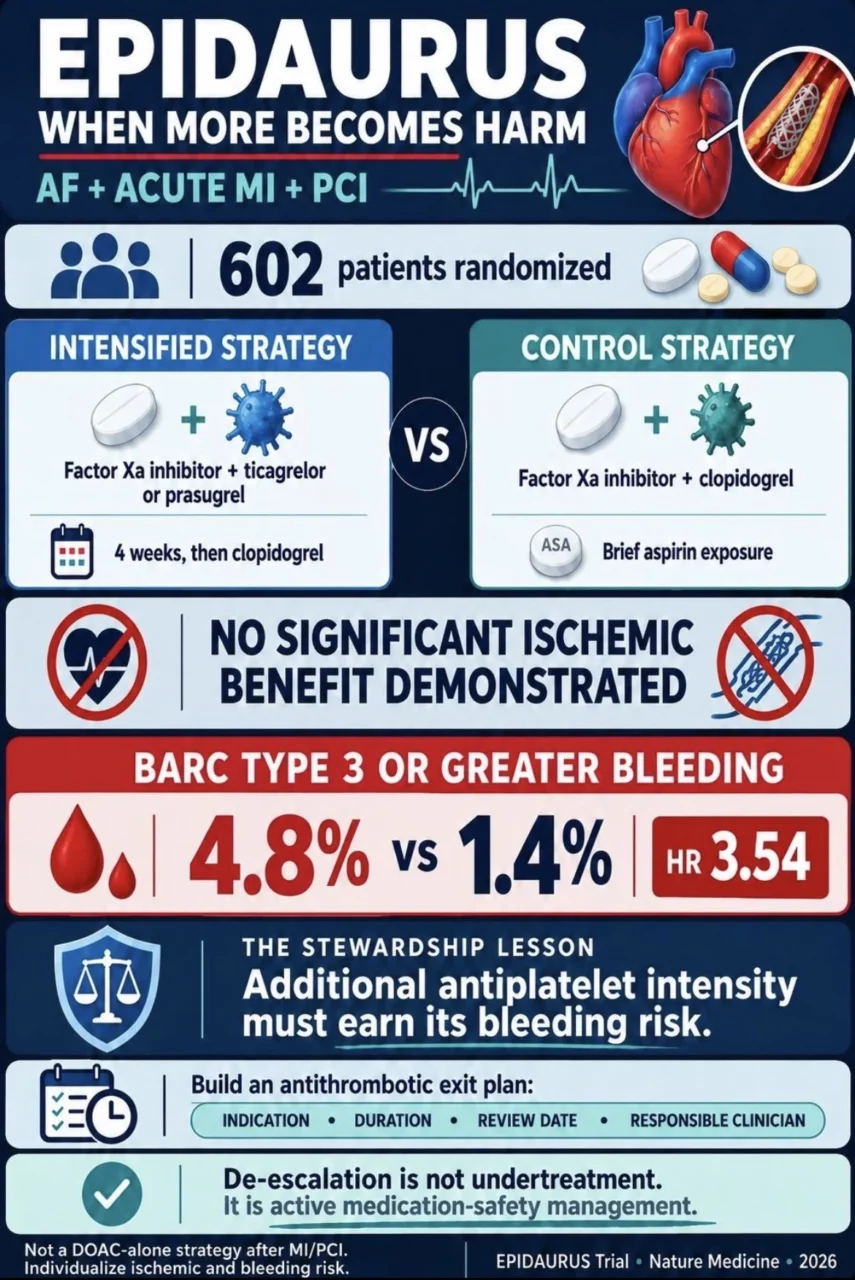
EPIDAURUS asked whether more potent platelet inhibition improves outcomes when a factor Xa inhibitor is already on board.
Investigators randomized 602 patients to:
- A factor Xa inhibitor plus ticagrelor or prasugrel for four weeks, followed by clopidogrel or
- A factor Xa inhibitor plus clopidogrel, with brief aspirin exposure primarily during hospitalization
The intensified strategy did not demonstrate superiority for the primary ischemic endpoint.
It did produce substantially more clinically important bleeding:
- BARC type 3 or greater bleeding: 4.8% vs 1.4%
- Hazard ratio: 3.54
- No significant reduction in the reported ischemic outcomes
Enrollment stopped after 602 of a planned 1,474 participants because superiority appeared unlikely and safety concerns were emerging.
The lesson is not that less treatment is always better – or that anticoagulation alone is sufficient immediately after MI and PCI.
It is that additional antiplatelet intensity must earn its bleeding risk.
EPIDAURUS reinforces a broader stewardship framework:
- After AF-associated PCI, avoid unnecessarily prolonged triple therapy.
- When anticoagulation and a P2Y12 inhibitor are combined, clopidogrel remains preferred for most patients.
- Reassess therapy as coronary risk stabilizes.
- In appropriate patients with AF and stable chronic coronary disease, anticoagulant monotherapy may provide a better balance than continuing an antiplatelet indefinitely.
The trial ended early and cannot settle every ischemic question. Selected patients with exceptionally high stent-thrombosis or procedural risk may require a different approach.
But ‘just in case’ is not a duration plan.
Every patient discharged on multiple antithrombotic agents should have an exit plan:
- Indication for each medication
- Intended duration and review date
- Clinician responsible for reassessment
- Earlier review if bleeding, renal decline, interactions, or procedures change the balance
Planned de-escalation is not undertreatment. It is an active medication-safety intervention.
Does your discharge process document who will reassess each antithrombotic agent – and when?
Views are my own and do not represent the Department of Veterans Affairs.”
Find more posts featuring Edward Lee Carter on Hemostasis Today.
-
Oct 19, 2026, 19:44Where You Live Should not Determine Whether You Receive Care – World Federation of Hemophilia
-
Oct 19, 2026, 19:42Belen Bianco: Prevention, Early Suspicion and an Interdisciplinary Approach Save Lives
-
Oct 19, 2026, 19:40Christina Chrysohoou: Catheter-Based LAAC vs OAC for Stroke Prevention in Atrial Fibrillation
-
Oct 19, 2026, 19:38Matthew Flick: A Two-Day Research Meeting on Fibrinogen, Hemostasis and Thrombosis
-
Oct 19, 2026, 19:37Hayat Saeed: Excited to Share Our Publication on the FGL1–Hepcidin Axis in Iron Homeostasis and Disease
-
Oct 19, 2026, 19:08IPAW 2026 Comes to a Close, but the Work Continues – PPTA
-
Oct 19, 2026, 17:44Paul Riley: Moderating a Webinar on Anticoagulation Monitoring
-
Oct 19, 2026, 16:36Christopher Pittman: Blood Clot Prevention Cannot End at Hospital Discharge
-
Oct 19, 2026, 16:13Javier M. Floren: When Immune Cells Move With Their Environment