


Islam Arid: Why We Say ‘Time is Brain’ when It’s Coming to Stroke Management?
Islam Arid, Registered Nurse at Memorial Hermann Health System, shared a post on LinkedIn:
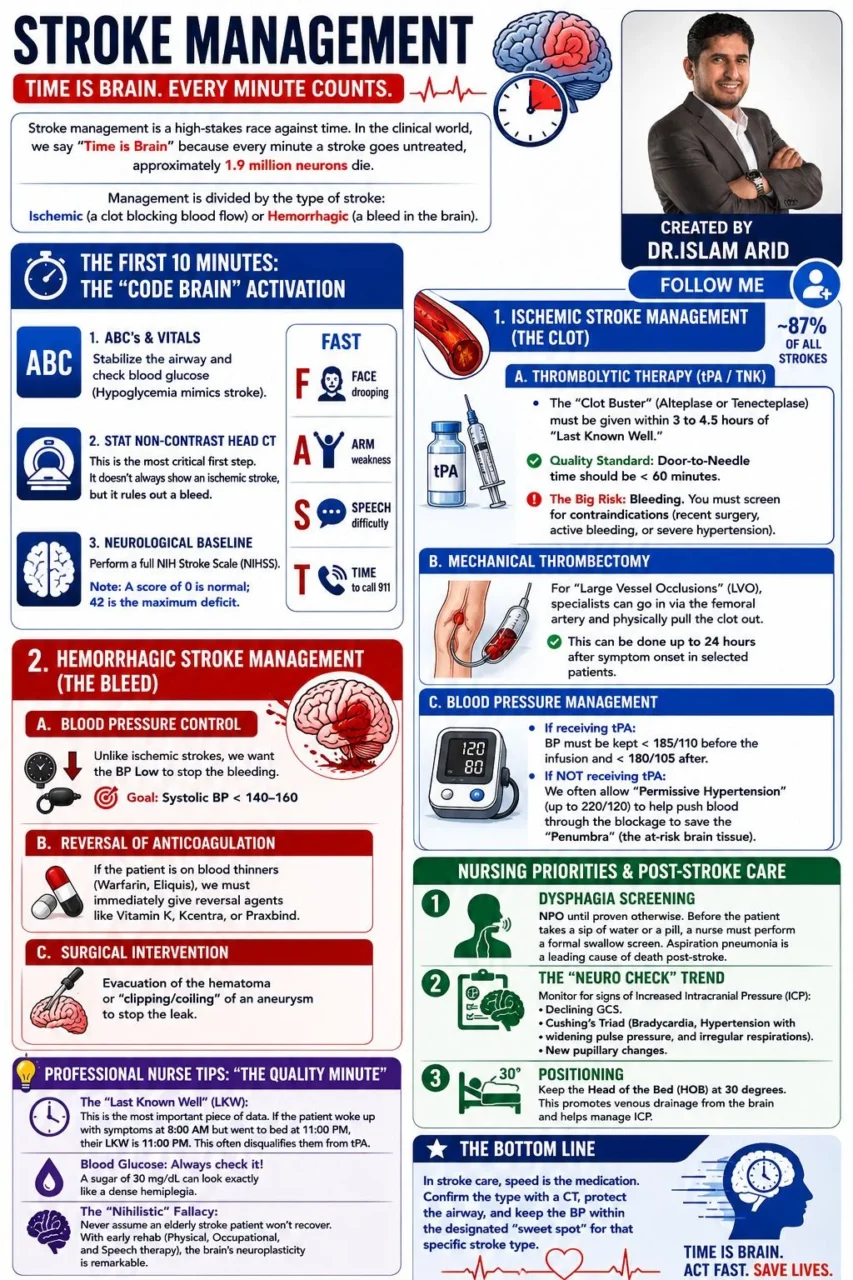
“Stroke management is a high-stakes race against time.
In the clinical world, we say ‘Time is Brain’ because every minute a stroke goes untreated, approximately 1.9 million neurons die.
Management is divided by the type of stroke: Ischemic (a clot blocking blood flow) or Hemorrhagic (a bleed in the brain).
The First 10 Minutes: The ‘Code Brain’ Activation
When a patient presents with stroke symptoms (FAST: Face drooping, Arm weakness, Speech difficulty, Time to call), the ‘Quality’ goal is a rapid, standardized assessment.
- ABC’s and Vitals: Stabilize the airway and check blood glucose (Hypoglycemia mimics stroke).
- Stat Non-Contrast Head CT: This is the most critical first step. It doesn’t always show an ischemic stroke, but it rules out a bleed.
- Neurological Baseline: Perform a full NIH Stroke Scale (NIHSS).
- Note: A score of 0 is normal; 42 is the maximum deficit.
1. Ischemic Stroke Management (The Clot)
About 87% of all strokes.
A. Thrombolytic Therapy (tPA / TNK)
The ‘Clot Buster’ (Alteplase or Tenecteplase) must be given within 3 to 4.5 hours of ‘Last Known Well.’
- Quality Standard: Door-to-Needle time should be < 60 minutes.
- The Big Risk: Bleeding. You must screen for contraindications (recent surgery, active bleeding, or severe hypertension).
B. Mechanical Thrombectomy
For ‘Large Vessel Occlusions’ (LVO), specialists can go in via the femoral artery and physically pull the clot out.
This can be done up to 24 hours after symptom onset in selected patients.
C. Blood Pressure Management
- If receiving tPA: BP must be kept < 185/110 before the infusion and < 180/105 after.
- If NOT receiving tPA: We often allow ‘Permissive Hypertension’ (up to 220/120) to help push blood through the blockage to save the ‘Penumbra’ (the at-risk brain tissue).
2. Hemorrhagic Stroke Management (The Bleed)
Caused by a ruptured aneurysm or uncontrolled hypertension.
A. Blood Pressure Control
Unlike ischemic strokes, we want the BP Low to stop the bleeding. The goal is typically a Systolic BP < 140–160.
B. Reversal of Anticoagulation
If the patient is on blood thinners (Warfarin, Eliquis), we must immediately give reversal agents like Vitamin K, Kcentra, or Praxbind.
C. Surgical Intervention
Evacuation of the hematoma or ‘clipping/coiling’ of an aneurysm to stop the leak.
Nursing Priorities and Post-Stroke Care
1. Dysphagia Screening
NPO until proven otherwise.
Before the patient takes a sip of water or a pill, a nurse must perform a formal swallow screen.
Aspiration pneumonia is a leading cause of death post-stroke.
2. The ‘Neuro Check’ Trend
Monitor for signs of Increased Intracranial Pressure (ICP):
- Declining GCS.
- Cushing’s Triad (Bradycardia, Hypertension with widening pulse pressure, and irregular respirations).
- New pupillary changes.
3. Positioning
Keep the Head of the Bed (HOB) at 30 degrees.
This promotes venous drainage from the brain and helps manage ICP.”
Stay updated with Hemostasis Today.
-
Nov 15, 2026, 04:31Aakriti Gupta: Anticoagulation for Leaflet Thickening After TAVR
-
Nov 14, 2026, 23:57Jamie S. Y. Ho: Exploring the Mechanisms of Arterial Thrombosis and the Evolution of Antithrombotic Therapy
-
Nov 14, 2026, 23:53Jacopo Imberti: The Past, Present and Future of Arterial Thrombosis Research
-
Nov 14, 2026, 23:48Shrouk Ramadan: Joining the Editorial Review Board of Clinical and Applied Thrombosis and Hemostasis
-
Nov 14, 2026, 23:46Habib Bennaceur: Moving Towards Fewer Limitations for People Living With Haemophilia
-
Nov 14, 2026, 23:44Paul Healy: EU Approves Frehemgo for Haemophilia A
-
Nov 14, 2026, 23:43Mehak Trehan: ASH 2026 Benign Hematology – Ten Abstracts Through an Indian Lens
-
Nov 14, 2026, 23:33Felipe Magalhaes Furtado: Artificial Intelligence Advances PNH Clone Detection Through Machine Learning
-
Nov 14, 2026, 23:33Mona Alfaraj: International Pathology Day Promotes Education in Hemoglobinopathy Diagnostics