


Ney Carter Borges: Low-Dose Rivaroxaban in Advanced Chronic Kidney Disease – Lessons From the TRACK Trial
Ney Carter Borges, Member Cardiologist of Global Physician Association at Cleveland Clinic Florida, shared a post on LinkedIn:
“Low-Dose Rivaroxaban in Advanced Chronic Kidney Disease: Lessons From the TRACK Trial
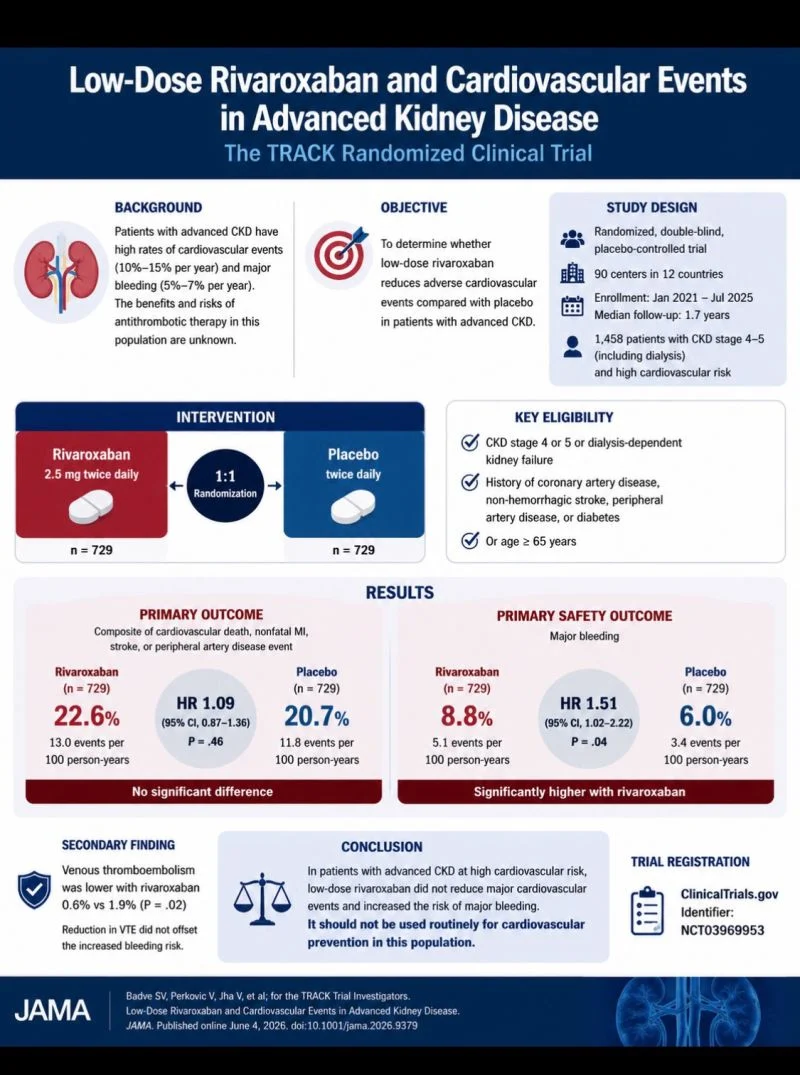
The TRACK trial evaluated whether low-dose rivaroxaban (2.5 mg twice daily) could reduce major cardiovascular events in patients with advanced chronic kidney disease (CKD stage 4–5), including those receiving dialysis. A total of 1,458 high-risk patients were randomized to rivaroxaban or placebo and followed for a median of 1.7 years.
The primary composite endpoint—cardiovascular death, myocardial infarction, stroke, or peripheral artery disease events—occurred in 22.6% of patients receiving rivaroxaban compared with 20.7% of those receiving placebo (HR 1.09; 95% CI 0.87–1.36; p=0.46), demonstrating no cardiovascular benefit. Importantly, all-cause mortality and individual cardiovascular outcomes were also not significantly improved with rivaroxaban therapy.
In contrast, major bleeding events were significantly more frequent in the rivaroxaban group (8.8% vs 6.0%; HR 1.51; 95% CI 1.02–2.22; p=0.04). Although venous thromboembolism occurred less frequently with rivaroxaban, this benefit did not translate into an overall favorable net clinical outcome because of the increased bleeding risk.
These findings differ from earlier studies such as COMPASS and VOYAGER PAD, where low-dose rivaroxaban combined with aspirin improved cardiovascular outcomes.
The TRACK investigators suggest that the unique pathophysiology of advanced CKD—including severe vascular disease, chronic inflammation, endothelial dysfunction, and heightened bleeding susceptibility—may limit the effectiveness of antithrombotic strategies in this population.
Take-Home Message: In patients with advanced CKD or dialysis-dependent kidney failure, low-dose rivaroxaban should not be routinely used for cardiovascular event prevention.
The therapy failed to reduce major cardiovascular outcomes while significantly increasing major bleeding, emphasizing the need for CKD-specific cardiovascular prevention strategies.”
Other posts featuring Ney Carter Borges on Hemostasis Today.
-
Oct 16, 2026, 16:01Obi Light Ogbonnia: The Greatest Reward Is Changing Lives, Not Winning Awards
-
Oct 16, 2026, 15:18Carmine Liberatore: Limited Accuracy of VTE Risk Scores in Multiple Myeloma
-
Oct 16, 2026, 14:55Alex Borstein and the Bleeding Phenotype of Hemophilia A Carriers
-
Oct 16, 2026, 13:59Aya Akmal Amin: Antiphospholipid Syndrome Management and Risk Stratification
-
Oct 16, 2026, 13:10Emanuel Sueldo: CAHT 2026 Celebrates Scientific Progress and Team Achievements
-
Oct 16, 2026, 13:05Maha Othman: Queen’s Health Sciences Advances CAT Risk Models and Pediatric ISTH-BAT Cut-Offs
-
Oct 16, 2026, 13:03Thrombosis Awareness Must Lead to Timely Action – Roche
-
Oct 16, 2026, 12:49Wolfgang Miesbach: 5-Year CBDR Data Confirms Emicizumab Safety and Efficacy in Hemophilia A
-
Oct 16, 2026, 12:40Edward Lee Carter: How Factor XI Inhibition Could Transform Anticoagulation Therapy