


Samwel Mikaye/LinkedIn
Mar 4, 2026, 15:46
Samwel Mikaye։ Key Insights on Stroke Types, Diagnosis, and Management
Samwel Mikaye, Medical Doctor at MSK, shared a post on LinkedIn:
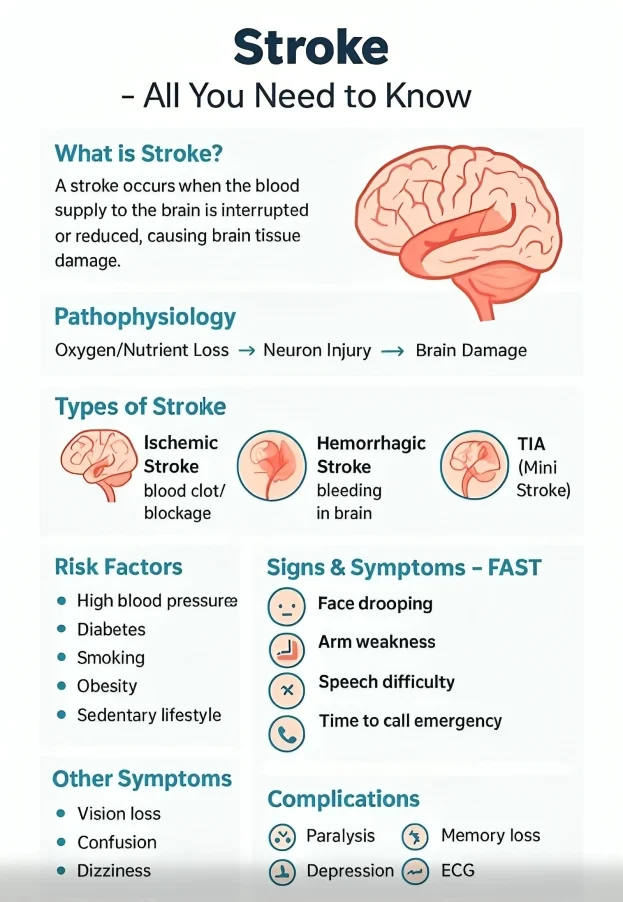
”Stroke (Cerebrovascular Accident – CVA)
Definition
- Sudden onset of neurological deficit due to interruption of blood flow to the brain, lasting >24 hours or causing death, with vascular origin.
Types of Stroke
1. Ischemic Stroke (≈85%)
- Cause: Thrombosis, embolism, systemic hypoperfusion
- Subtypes: Large artery atherosclerosis, cardioembolic, small vessel (lacunar)
- Risk factors: Hypertension, diabetes, atrial fibrillation, smoking
2. Hemorrhagic Stroke (≈15%)
- Cause: Rupture of a blood vessel
- Types:
– Intracerebral hemorrhage – often due to hypertension
– Subarachnoid hemorrhage – often due to aneurysm rupture
– Risk factors: Hypertension, aneurysms, anticoagulation, trauma
Clinical Features
Depends on brain area affected:
- Sudden weakness or numbness (face, arm, leg), usually one side
- Speech difficulties: Aphasia (expressive/receptive)
- Visual changes: Hemianopia, blurred vision
- Coordination problems: Ataxia, dizziness
- Severe headache: Common in hemorrhagic stroke
Other signs:
- Facial droop, limb weakness, difficulty walking, altered consciousness
Diagnosis
1. Immediate: Clinical assessment (FAST: Face, Arm, Speech, Time)
2. Imaging:
- CT scan non-contrast – differentiates ischemic vs hemorrhagic
- MRI – more sensitive for early ischemia
3. Lab tests: CBC, electrolytes, coagulation profile, glucose, cardiac enzymes (if cardioembolic suspected)
Management
Ischemic Stroke:
- Acute: Thrombolysis (IV tPA within 4.5 hours), mechanical thrombectomy (large vessel occlusion)
- Secondary prevention: Antiplatelets, anticoagulation if atrial fibrillation, statins, blood pressure control
Hemorrhagic Stroke:
- Acute: Blood pressure control, reversal of anticoagulation, surgical intervention if needed
- Supportive care: ICP management, seizure control
All strokes:
- Supportive: Airway, fluids, glycemic control, physiotherapy, nutrition
Complications
- Cerebral edema, raised ICP
- Seizures
- Recurrent stroke
- Functional deficits: hemiplegia, aphasia, cognitive impairment
- Early recognition and imaging are critical – ‘time is brain.’
- Ischemic vs hemorrhagic stroke determines treatment; do not give anticoagulants until confirmed.
- Multidisciplinary rehab improves functional outcomes.”
Other posts featuring Samwel Mikaye on Hemostasis Today.
-
Oct 18, 2026, 02:43Priya Sriskandarajah: Diagnosis and Management of PV and JAK2-Unmutated Erythrocytosis
-
Oct 18, 2026, 02:41C. Michael Gibson: A Meta-Analysis of DOACs and DAPT After Left Atrial Appendage Closure
-
Oct 18, 2026, 02:27What Hematologists Should Remember About the Person Behind the Platelet Count – ASH
-
Oct 18, 2026, 01:44Marta Velia Antonini: How to Deliver CRRT during ECMO?
-
Oct 18, 2026, 01:19Aamir Saeed: Anticoagulation, Cirrhosis, and Other Risk Factors for Post-ERCP Bleeding
-
Oct 18, 2026, 00:33Elad Asher: Does Opening the Clot Change How a Patient Feels Three Months Later?
-
Oct 18, 2026, 00:22Richa Sharma: Evaluating Heterogeneity in Anticoagulation Treatment Effects in Cryptogenic Stroke
-
Oct 18, 2026, 00:07Irem Karaman Sebin: The Evidence Favoring Warfarin in High-Risk Antiphospholipid Syndrome
-
Oct 18, 2026, 00:07Emma Stevens: Lighting Up Buildings in Red and Blue for World Thrombosis Day