


Mohamed Magdy Badr: Calciphylaxis – The Silent Killer in Kidney Failure
Mohamed Magdy Badr, Wound Care Consultant at Armed Force Rehabilitation Center, posted on LinkedIn:
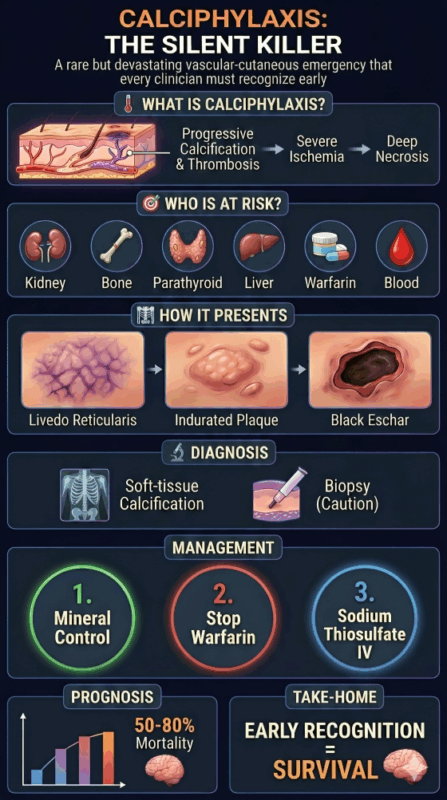
”Calciphylaxis: The Silent Killer in Kidney Failure
A rare but devastating vascular-cutaneous emergency that every clinician must recognize early.
What Is Calciphylaxis?
Calciphylaxis is a life-threatening syndrome caused by progressive calcification, thrombosis, and occlusion of small dermal and subcutaneous arterioles.
The result? Severe ischemia → deep necrosis → non-healing ulcers with extremely high mortality.
Who Is at Risk?
- Most commonly seen in patients with:
- End-Stage Renal Disease (ESRD) on dialysis
- Disturbed calcium–phosphate balance
- High PTH (secondary hyperparathyroidism)
- Diabetes, obesity, liver disease
- Warfarin therapy
- Low serum albumin
How It Presents Clinically
Calciphylaxis lesions typically evolve through:
- Painful violaceous livedo reticularis
- Indurated plaques or nodules
- Ulceration with black eschar (necrosis)
- Risk of rapid infection, sepsis, and limb loss
Key red flag: Pain is often out of proportion to the visible lesion.
Common sites: thighs, abdomen, buttocks, legs—areas rich in adipose tissue.
Diagnosis
- Primarily clinical, supported by:
- Elevated Ca × PO₄ product
- Increased PTH
- Imaging showing soft-tissue calcification
- Biopsy only when necessary (may worsen the wound)
Management: Multidisciplinary and Urgent
Successful management requires rapid, coordinated intervention:
1. Correct Mineral Imbalance
- Phosphate binders
- Aggressive control of Ca/PO₄
- Cinacalcet for PTH regulation
2. Discontinue Warfarin
- One of the most evidence-based steps.
3. Sodium Thiosulfate
- IV infusion after hemodialysis—now a cornerstone therapy.
4. Optimal Wound Care
- Gentle debridement
- Infection prevention
- Moisture balance
- Pain management (often severe)
5. Consider Parathyroidectomy
- For refractory secondary hyperparathyroidism.
Prognosis
- Mortality remains 50–80%, mainly due to sepsis.
- Early detection and aggressive treatment dramatically improve survival.
Take-Home Message
- Any dialysis patient with severe, disproportionate pain, violaceous patches, or evolving necrotic ulcers should raise immediate suspicion for calciphylaxis.
- Early recognition = better outcomes.
- Delayed recognition = catastrophic consequences.”
Stay informed with Hemostasis Today.
-
Oct 23, 2026, 07:17Nahush Chafekar: Anticoagulation Strategies in Haemodialysis Patients with AF
-
Oct 23, 2026, 07:15Jessica Garcia: Honored Among the Best Doctors of 2026
-
Oct 23, 2026, 07:07Reda Awad Abdelsalam: FXIa Inhibition for Stroke Prevention
-
Oct 23, 2026, 06:43Tim Blair: Improving DVT Awareness, Early Diagnosis, and Access to Treatment
-
Oct 22, 2026, 18:04Basem Goueli: Blood Clots in the NFL
-
Oct 22, 2026, 17:57Syed Ahmed: Viral Triggers of Immune Thrombocytopenia and Thrombosis
-
Oct 22, 2026, 17:49Valerie Tutwiler: Bridging Engineering and Medicine to Advance Thrombosis Research
-
Oct 22, 2026, 17:41Jesus Ardila Novoa: How Patient Education Can Transform Hemophilia Care
-
Oct 22, 2026, 17:30Filipe Gonçalves: Advancing Bleeding Disorder Diagnosis Through Multidisciplinary Collaboration